Breaking New Ground with AI in Intensive Patient Care
Dr. Andrew Kramer's team reports that showing ICU clinicians a machine-learning warning score, ViSIG, was linked to shorter ICU stays, less ventilation time and fewer readmissions.


Enhancing patient outcomes in Intensive Care Units (ICUs) has catalyzed the development of predictive algorithms designed to provide patient-specific alerts at the bedside, making a significant advance towards the future of proactive critical care. Despite the potential, the journey has encountered obstacles, notably using retrospectively collected data, which often led to performance metrics that did not reflect their real-world efficacy. The lack of models tested in real-world settings highlighted a significant gap in efforts to improve patient care. Against this backdrop, ViSIG stands out as a groundbreaking pattern recognition system aimed at detecting early signs of potential mortality in ICU patients. This innovative approach, using genetic algorithms to detect changes in vital signs indicative of underlying physiologic decline, is set to redefine patient management and care in adult critical care environments.
A landmark study conducted by Dr. Andrew Kramer from Prescient Healthcare Consulting, in collaboration with Dr. Marc LaFonte and Dr. Ibrahim El Husseini from Robert Wood Johnson-Barnabas University Hospital, Simon Didcote from OBS Medical Ltd, Paula Maurer from Medical Decision Network, and Dr. Frantz Hastrup and Dr. James Krinsley from Stamford Hospital, has shed light on ViSIG’s effectiveness. Their significant work, published in Informatics in Medicine Unlocked, emphasizes the system’s role in transforming ICU patient care.
“Our aim was to harness the predictive power of machine learning to empower clinicians with the information needed to make informed decisions,” states Dr. Kramer, highlighting the extensive collaboration across six adult ICUs in two U.S. hospitals to analyze ViSIG’s impact.
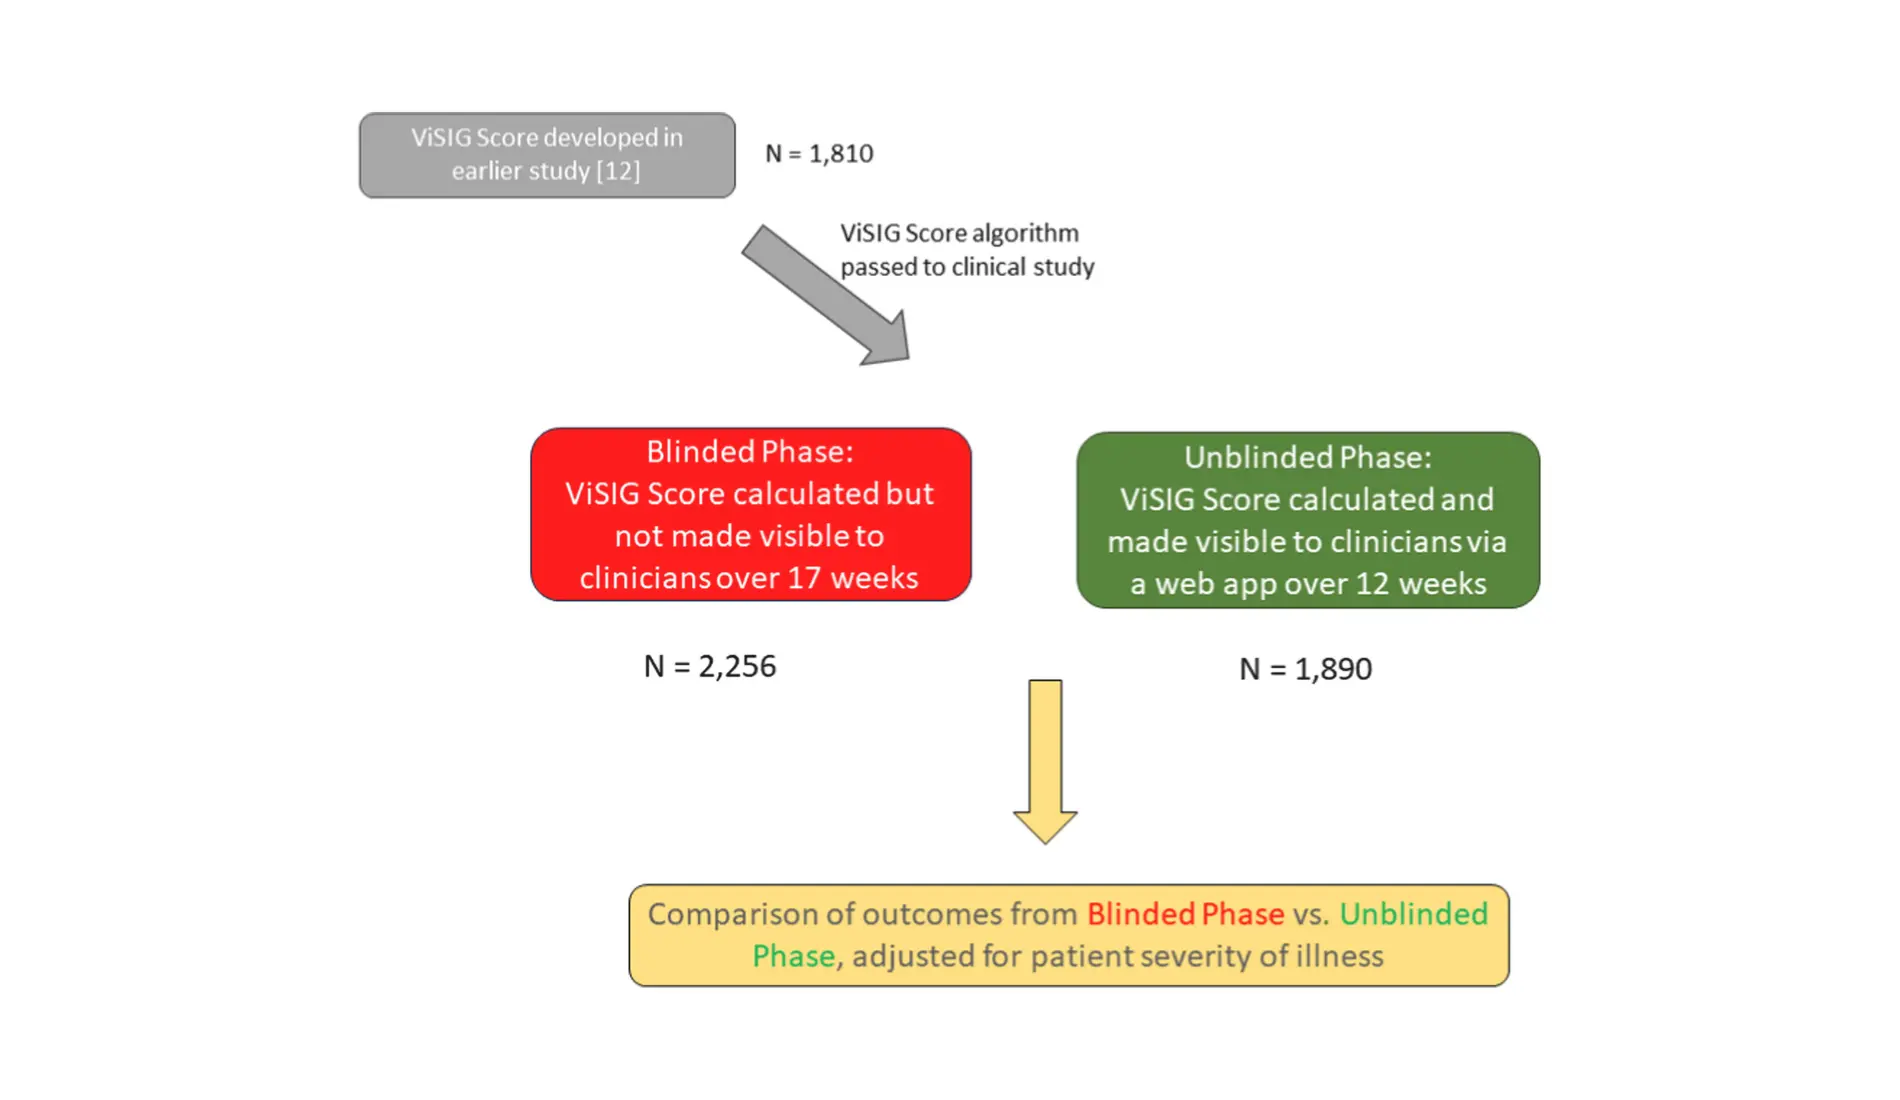
A previous investigation (Critical Care Medicine, October 2013) had validated the predictive accuracy of the algorithm underlying ViSIG, with higher scores strongly associated with increasing mortality risk. The current study utilized a two-phase methodology to evaluate ViSIG’s clinical utility. Initially, clinicians were blind to the system’s scores before introducing a phase where these scores were accessible via a user-friendly interface. “The study was meticulously designed to measure the system’s impact on clinical outcomes,” Dr. Kramer notes.
ViSIG’s predictive model relies on the continuous monitoring of vital signs and mechanical ventilation status, yielding a composite score with three levels of mortality risk. This score is easy to interpret and is updated every 30 minutes, making it timely. “This approach enabled us to provide evidence of patient decline before it is manifested clinically, hopefully reducing unexpected deleterious outcomes,” explains Dr. Kramer, stressing the importance of testing ViSIG’s advanced algorithm in real-world situations.
The findings of the study are striking, demonstrating significant improvements in patient care. “The adoption of ViSIG into clinical workflows could significantly improved outcomes, particularly in reducing the duration of ICU stays and mechanical ventilation,” Dr. Kramer reports. The study also observed a substantial decrease in ICU readmissions, showcasing ViSIG’s capability to enhance immediate care as well as promote long-term patient health. Dr. Andrew Kramer and his team’s work demonstrates the benefits of integrating machine learning tools like ViSIG into the critical care setting. By providing clinicians with real-time insights into patients’ conditions, ViSIG supports informed clinical decision-making, leading to markedly improve patient outcomes.
About the researchers

Dr. Andrew Kramer
Dr. Andrew Kramer has been actively involved in critical care research for the past 22 years. He is a co-developer of the APACHE IV, APACHE IVa, MPM-III, and OASIS severity of illness systems, resulting in over 100 predictive models that are in use worldwide.… Additionally, he’s been an author of over 80 manuscripts in high-impact journals, including two that have garnered over 500 citations. Dr. Kramer received his a PhD in Human Genetics from the Medical College of Virginia. Afterward, he underwent a post-doctoral fellowship in Epidemiology. Dr. Kramer joined Cerner Corporation in 2003 and worked there until 2015, leading the company’s critical care research efforts. In 2015, he left Cerner to establish Prescient Healthcare Consulting, a company focused on delivering novel analytic solutions in critical care.

Dr. James Krinsley
Dr. James Krinsley graduated from Yale College and Cornell University Medical College. He completed training in Internal Medicine at New York University and Pulmonary-Critical Care Medicine at Yale University School of Medicine.… He was Director of Critical Care at Stamford Hospital from 1998-2020 and is Professor of Clinical Medicine at Columbia University Vagelos College of Physicians and Surgeons. He has published extensively on numerous aspects of glucose control in the critically ill since 2003, as well as on topics involving mechanical ventilation. A full listing of his publications can be found at: https://scholar.google.com/citations?user=uj0vccAAAAAJ&hl=en.
Journal reference
A.A. Kramer et al., “Prospective evaluation of a machine learning-based clinical decision support system (ViSIG) in reducing adverse outcomes for adult critically ill patients,” Informatics in Medicine Unlocked, 2024.